Ready to streamline healthcare?
Discover how our platform transforms operations. Book a free 30-min consultation to see it in action.
From Pilot to Production: How Healthcare Leaders Can Implement AI in Radiology

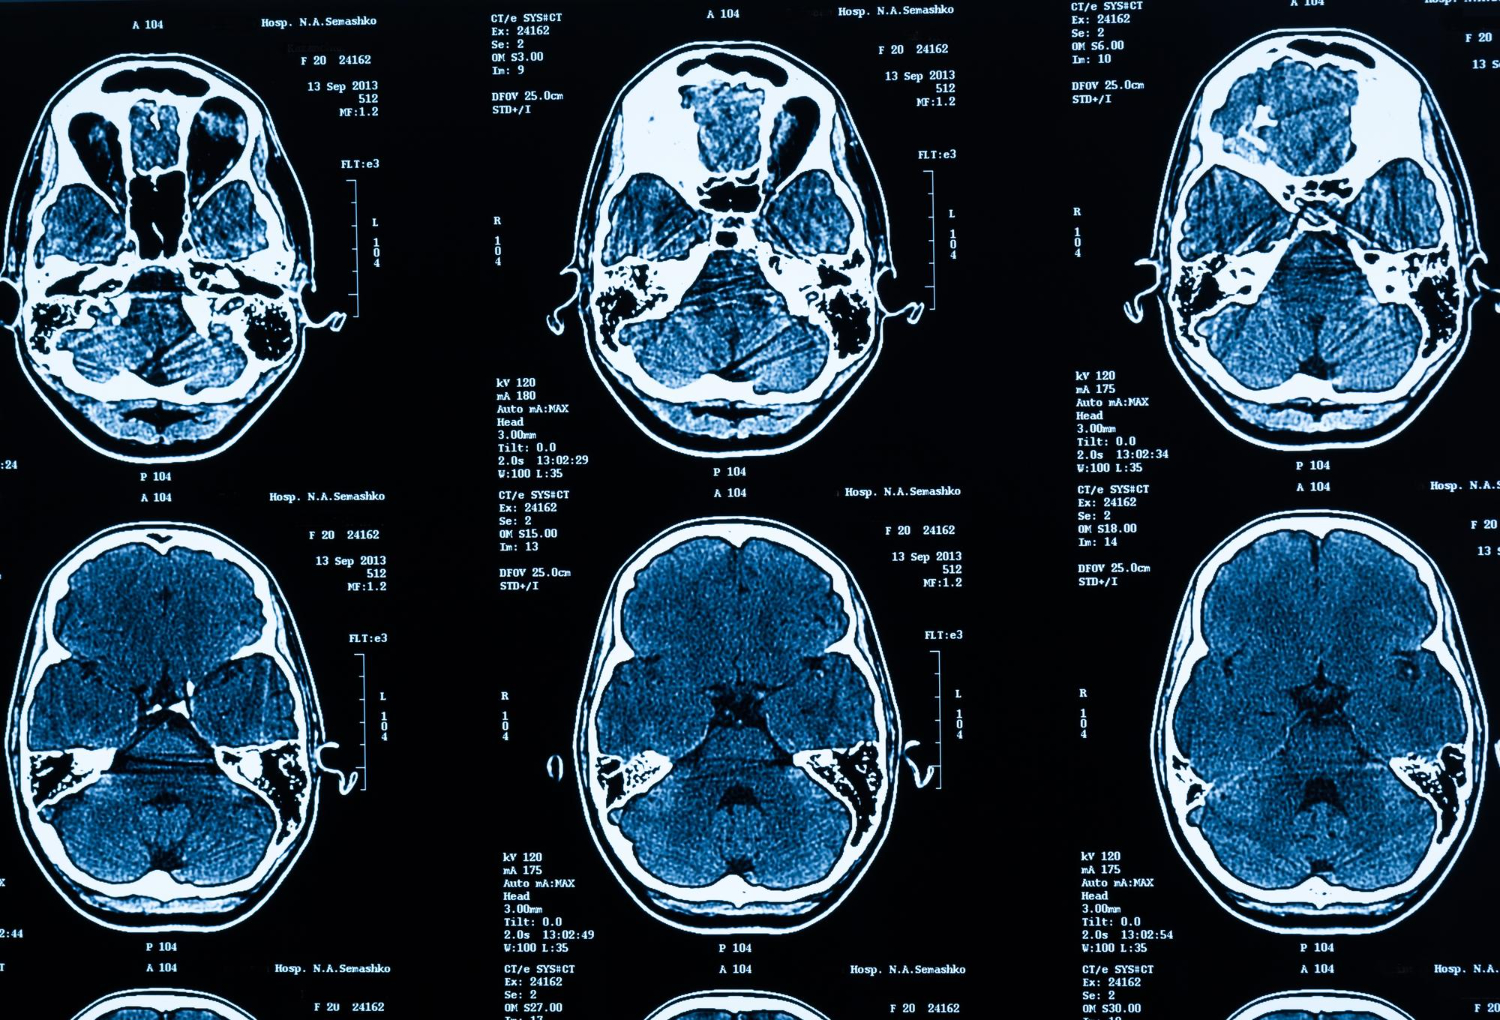
Artificial intelligence has moved quickly from research demonstrations into radiology departments, imaging centers, and distributed reading networks. The FDA reported more than 1,600 authorized AI-enabled medical devices across medical specialties as of September 2026, with radiology representing a substantial share of the device landscape.
Yet authorization and availability do not make implementation automatic. A tool can perform well in a study and still fall short in practice if it addresses the wrong problem, receives incomplete data, disrupts the radiologist's workflow, or lacks an owner after launch.
For healthcare leaders, the real work begins after the product demonstration. Moving from pilot to production requires clinical governance, local acceptance testing, technical integration, user training, performance monitoring, and a clear process for responding when results differ from expectations.
Why radiology AI pilots stall
Many AI projects begin with interest in the technology rather than agreement on the problem. A team may evaluate a tool because it performs an impressive task, while the department's actual constraint is reader coverage, missing priors, incomplete orders, or report-delivery failures.
Common reasons pilots do not reach production include:
- No clearly defined clinical or operational objective
- Limited radiologist involvement in selection
- A validation dataset that does not reflect local practice
- Poor integration with PACS, RIS, EHR, or worklists
- Too many false-positive alerts
- No downtime or fallback procedure
- Unclear ownership for post-launch monitoring
- Unbudgeted implementation and support costs
- User training that ends before the workflow changes
Successful adoption starts by treating AI as part of a clinical system, not as a stand-alone application.
1. Define the problem before reviewing products
Write a short problem statement that a clinical and operational team can measure. Examples include:
- Potentially urgent studies are not consistently reaching the front of the worklist.
- Manual measurements add substantial time to a high-volume examination.
- Reports contain recurring laterality or completeness issues.
- A backlog develops during a predictable coverage period.
- Radiologists spend excessive time retrieving priors or re-entering structured information.
Then document the current baseline. Depending on the problem, that might include turnaround time, worklist age, reporting time, alert volume, quality-review findings, incomplete-study rates, or user-reported workflow friction.
Without a baseline, an organization cannot tell whether the AI tool improved the workflow or simply added another system.
2. Form a multidisciplinary AI governance group
The American College of Radiology approved its first practice parameter for imaging AI in 2026. The parameter addresses governance, product selection, local acceptance testing, real-world performance monitoring, privacy, and the infrastructure needed for safe clinical use.
A radiology AI governance group may include:
- Radiologists who will use or be affected by the tool
- Radiology operations leaders
- Technologists
- Imaging informatics and IT teams
- Medical physicists when relevant
- Quality and patient-safety leaders
- Privacy, security, compliance, and legal representatives
- Procurement and finance stakeholders
- Clinical partners from emergency medicine or another affected service
The group should establish decision rights. Who approves a pilot? Who decides whether performance is acceptable? Who can pause the tool? Who receives a safety concern? These questions should be answered before deployment.
3. Confirm the intended use and regulatory status
Not every product marketed as AI is regulated in the same way. The FDA regulates medical devices, including AI-enabled medical-device functions, based on intended use and technological characteristics. Other software functions may fall into a different regulatory category.
For a device used in clinical care, review:
- The FDA authorization pathway
- The authorized indication and intended users
- Supported modalities and patient populations
- Required image types and technical conditions
- Known limitations and warnings
- Whether the function is assistive or autonomous
- The device version being purchased
- Any authorized predetermined change-control plan
FDA authorization is an important threshold, but it is not proof that the product will perform equally well with every scanner, protocol, patient population, disease prevalence, and workflow.
4. Evaluate evidence that matches the local setting
Look beyond a single performance number. Sensitivity and specificity may be important, but leaders also need to understand how the tool was tested and how it will be used.
Ask:
- Was the evaluation retrospective or prospective?
- Did it include multiple sites and equipment vendors?
- Were the patients similar to the local population?
- Was performance assessed for relevant subgroups?
- Was the device tested with the intended users?
- Did the study measure the combined human-AI workflow?
- Were false-positive and false-negative consequences evaluated?
- Were workflow outcomes measured in addition to algorithm performance?
A product intended to prioritize pulmonary embolism studies, for example, should be evaluated not only on detection performance but also on how alerts affect worklist order, radiologist attention, and care-team communication.
5. Design a local acceptance test
Local acceptance testing verifies that the product is installed correctly, receives the expected inputs, produces usable outputs, and fits the proposed workflow. It is not a substitute for the manufacturer's validation, and it should not become an unstructured attempt to re-create the entire regulatory review.
The test should reflect:
- Local scanner manufacturers and protocols
- Relevant patient and examination types
- Normal, abnormal, borderline, and technically limited studies
- Expected disease prevalence when feasible
- The real worklist and reporting environment
- User roles and access controls
- Interface failures and delayed data
- Downtime and recovery
- Cases outside the intended use
Define acceptance criteria before seeing the final results. This reduces the temptation to adjust the definition of success after the pilot begins.
6. Map the complete workflow
AI may touch the imaging process at order entry, acquisition, preprocessing, interpretation, reporting, communication, or quality review. Create a data-flow and workflow map that identifies:
- Where the input originates
- Which information is transmitted
- When the AI analysis begins
- How users know analysis is pending, complete, failed, or unavailable
- Where the output appears
- What action a user is expected to take
- How the action is documented
- What happens if the output conflicts with clinical judgment
An alert that appears in a separate portal may be technically functional but operationally ineffective if radiologists work in the PACS and never open the portal.
7. Integrate with PACS, RIS, EHR, and worklists
Technical integration should be designed around the user, not only the data connection. Review:
- Study and order matching
- DICOM and HL7 interfaces
- Worklist-priority changes
- Display of AI results and confidence information
- Identity and access management
- Report-template or structured-data connections
- Audit logs
- Data retention
- Cybersecurity controls
- Alerting for failed analysis
- Version tracking
Test the complete path from image acquisition through report delivery. A successful interface message does not prove that the right user saw the result at the right time.
8. Prepare for human factors and automation bias
AI changes attention. A user may rely too heavily on a positive alert, assume an unflagged study is normal, or spend extra time investigating false positives.
Training should explain:
- What the tool is designed to do
- What it cannot do
- Its intended-use population
- Common failure modes
- How to recognize an unavailable or incomplete result
- How to accept, edit, reject, or override output
- How to report a suspected problem
- The radiologist's continuing responsibility for interpretation
Training should be role-specific and repeated when the product or workflow changes.
9. Define downtime and fallback procedures
AI should not become a single point of failure. The department needs a safe workflow when the service is unavailable, slow, or producing results that appear unreliable.
A downtime plan should identify:
- How users learn that the service is unavailable
- Whether studies return to the standard worklist order
- Which manual checks resume
- Who contacts the vendor or internal support team
- How delayed results are handled
- Whether the tool must be revalidated after a major change
- How events are documented and reviewed
For a prioritization tool, users must understand that the worklist remains clinically active even when AI results are missing.
10. Monitor real-world performance
FDA lifecycle materials emphasize that performance considerations continue after deployment. The ACR practice parameter likewise includes real-world monitoring and continuous quality improvement.
Monitoring may include:
- Percentage of eligible studies analyzed
- Analysis failures and processing delays
- False-positive and false-negative review
- User acceptance, rejection, and override rates
- Turnaround time by priority
- Worklist-order changes
- Report amendments
- Quality-review findings
- Performance across relevant sites and patient groups
- User-reported workflow problems
- Changes following software updates
Set an expected review cadence and thresholds that trigger investigation. Monitoring data should be reviewed by people with clinical and technical authority to act.
11. Manage updates and performance drift
AI performance can change when scanner protocols, patient populations, referral patterns, prevalence, or upstream systems change. The product itself may also be updated.
Maintain a change log that records:
- Model and software versions
- Vendor release notes
- Interface changes
- Scanner or protocol changes
- Modified alert thresholds
- Training updates
- Acceptance-test results
- Performance concerns and corrective actions
Not every change requires the same level of testing, but the governance group should decide the level rather than leaving it to chance.
Radiologist-led implementation matters
AI can support worklist prioritization, measurements, reporting, and quality checks. It cannot replace the clinical context, communication, accountability, and judgment that radiologists bring to patient care.
Transparent Imaging is radiologist-led and built by radiologists, for radiologists. Its network of 200+ radiologists is subspecialty-focused, peer-reviewed, and technology-enabled. That structure supports flexible practice for radiologists and reliable coverage for imaging centers and hospital systems.
In an AI-enabled workflow, physicians should help define the problem, choose the tool, evaluate the output, and guide improvement after launch. Technology performs best when clinical leadership remains visible throughout the lifecycle.
Questions to ask before production deployment
- What measurable problem is this tool intended to solve?
- Is the proposed use consistent with the product's intended use?
- Does the evidence reflect our population and workflow?
- What did local acceptance testing show?
- How will users see and act on the output?
- What happens when the tool is unavailable?
- Which metrics will be monitored after launch?
- Who can pause or modify the deployment?
- How will vendor updates be reviewed?
- How will radiologists report concerns?
Frequently Asked Questions
1. Does FDA authorization mean local validation is unnecessary?
No. FDA authorization addresses the device for its intended use. Healthcare organizations still need to confirm installation, data flow, workflow fit, and acceptable performance in the local environment.
2. Who should lead a radiology AI implementation?
Leadership should be multidisciplinary, with active radiologist involvement. Clinical, operational, technical, security, quality, compliance, and financial perspectives may all be necessary.
3. How long should an AI pilot last?
There is no universal duration. The pilot should include enough representative cases, users, shifts, and operating conditions to evaluate the predefined objectives and risks.
4. What should happen if AI and the radiologist disagree?
The radiologist should independently evaluate the study and remain responsible for the final interpretation. The disagreement may also need to enter the tool-monitoring or quality-review process.
5. When should an AI tool be paused?
Pause criteria should be established before launch. Examples may include unexpected performance degradation, unsafe output, a material interface failure, or an unreviewed product change.
Move from experimentation to accountable clinical use
AI implementation succeeds when a defined problem, qualified users, connected systems, and continuing oversight work together. To discuss radiologist-led, technology-enabled imaging support, visit Transparent Imaging's Imaging Needs page or learn more about Transparent Imaging.
References
- FDA: Artificial Intelligence-Enabled Medical Devices
- FDA: AI-Enabled Medical Device List
- FDA: AI-Enabled Device Software Functions Lifecycle Guidance
- ACR-SIIM Practice Parameter for Imaging Artificial Intelligence
- ACR: First Practice Parameter for Imaging AI
- NIST AI Risk Management Framework